
Deep Gluteal Pain Syndrome: Diagnosis, Differentiation and Non-Surgical Management
Pain Spa Clinical Education
Deep Gluteal Syndrome: When Sciatica Doesn’t Start in the Spine
A practical guide to the causes, examination, imaging and non-surgical management of sciatic nerve entrapment in the deep gluteal space: piriformis syndrome, ischiofemoral impingement, gemelli–obturator internus syndrome, proximal hamstring syndrome and fibrous bands.
What is deep gluteal syndrome?
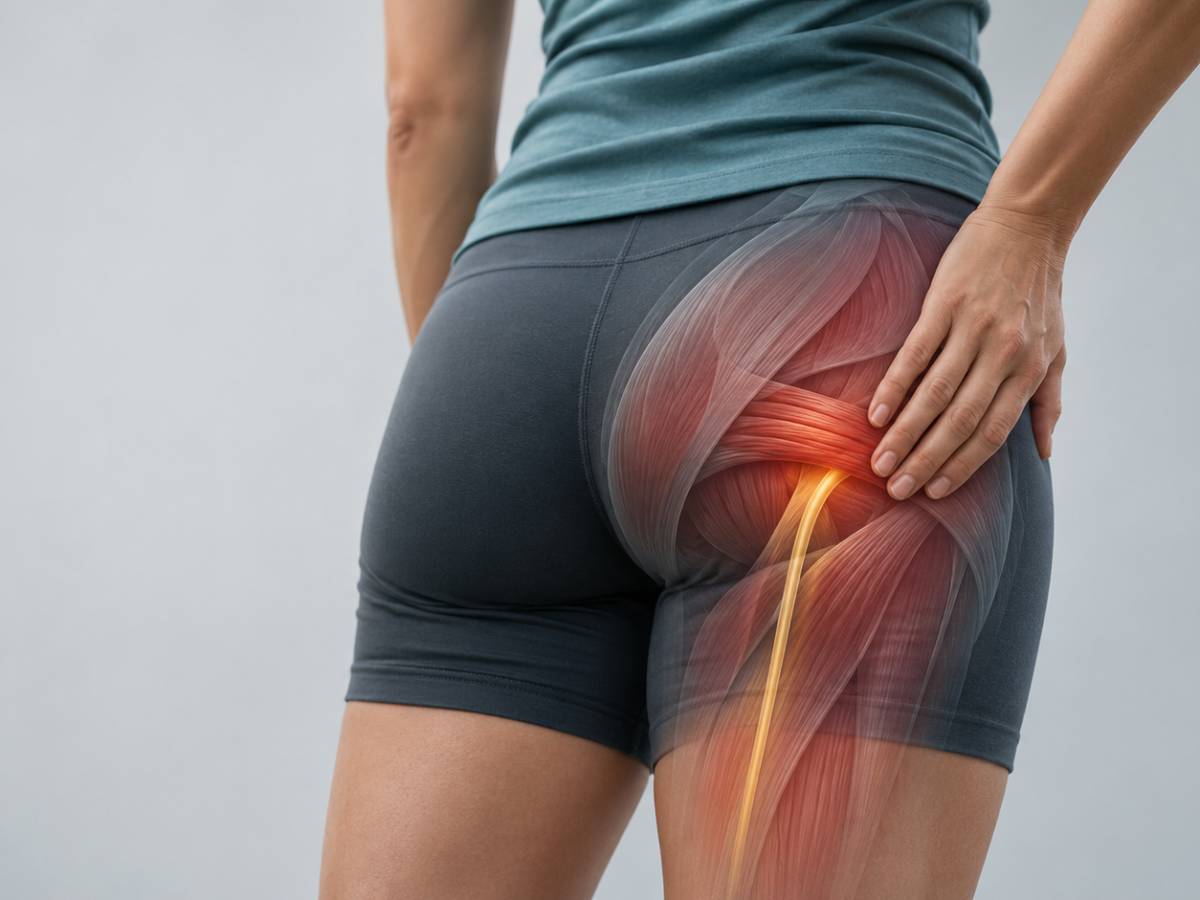
Deep gluteal syndrome (DGS) describes buttock and posterior hip pain caused by non-discogenic, extrapelvic entrapment of the sciatic nerve (and sometimes other nerves) within the deep gluteal, or subgluteal, space. It is often called “non-discogenic sciatica”.
DGS is an umbrella term. It grew out of the older concept of piriformis syndrome, which is now regarded as only one of several subtypes. Others include ischiofemoral impingement, gemelli–obturator internus syndrome, proximal hamstring (ischial tunnel) syndrome and entrapment by fibrous or fibrovascular bands.
Lumbar spine MRI is highly sensitive for disc and degenerative changes. As a result, patients with an extrapelvic entrapment are often labelled with “sciatica from the back”, sometimes after normal or incidental spinal imaging. Recognising DGS avoids unnecessary spinal intervention and opens up targeted treatment.
“Many of the patients we see with deep gluteal pain have already had a spinal MRI and been told their sciatica comes from the back. When the examination doesn’t fit, it is worth looking further down the course of the nerve.”
At a glance
- DGS is a diagnosis of exclusion, and there is no single gold-standard test.
- Typical features are deep buttock pain, intolerance of sitting for more than 20–30 minutes, and radiation down the posterior thigh. Root-level neurological deficits are usually absent.
- The site of pain and the hip position that provokes it help identify the culprit structure.
- Lumbar MRI comes first. Pelvic MRI or MR neurography then localises the problem, and a selective image-guided diagnostic injection confirms it.
- Management is stepwise: education, load modification and rehabilitation; then image-guided injection; then botulinum toxin in selected cases. Surgery is reserved for refractory, injection-confirmed cases.
From “piriformis syndrome” to deep gluteal syndrome
In 1928, Yeoman described sciatica arising from the sacroiliac joint, the piriformis muscle and the adjacent branches of the sciatic nerve. For decades afterwards, almost any non-discogenic buttock and leg pain was attributed to the piriformis. Before endoscopic exploration was possible, the label rested on clinical impression, and there were no agreed criteria or specific tests.
Periarticular hip endoscopy has changed this picture. Surgeons can now inspect the whole course of the sciatic nerve through the subgluteal space. Many causes of entrapment turn out to have little to do with the piriformis, most notably fibrous and fibrovascular bands. “Deep gluteal syndrome” was adopted to reflect this broader, multifactorial picture.
Is piriformis syndrome overdiagnosed?
Several authors argue that it is. In a review of 18 studies and over 6,000 cadavers, the prevalence of piriformis–sciatic nerve anomalies was 16.9%, almost identical to the 16.2% found in “surgical cases”. In an MRI study of 783 patients, there was no significant difference in buttock pain, sciatica or piriformis syndrome between patients with normal and variant nerve anatomy.
The lesson for clinicians is that an anatomical variant on imaging is not, by itself, proof of causation. The diagnosis should rest on a consistent clinical picture, imaging that agrees with it, and ideally a positive response to a targeted diagnostic block.
Anatomy of the deep gluteal space
The deep gluteal space is the fatty, cellular layer between the middle and deep gluteal fascia, lying beneath the gluteus maximus. The piriformis occupies a central position and is the key landmark. Above and below it, the neurovascular structures leave the pelvis through the greater sciatic foramen. These include the sciatic, superior and inferior gluteal, pudendal and posterior femoral cutaneous nerves, and the nerves to obturator internus and quadratus femoris.
Below the piriformis lie the short external rotators: the superior gemellus, obturator internus, inferior gemellus and quadratus femoris. The sciatic nerve runs over them, passing between the ischial tuberosity and the greater trochanter, about 1.2 cm from the lateral edge of the ischial tuberosity. Under normal conditions the nerve slides and stretches with hip movement. During a straight-leg raise it moves roughly 28 mm at 70–80° of hip flexion. Anything that tethers or compresses it can produce symptoms.
Table 1. Borders and contents of the deep gluteal space
| Border | Structure |
|---|---|
| Posterior | Gluteus maximus |
| Anterior | Posterior border of the femoral neck |
| Medial | Sacrotuberous ligament and falciform fascia |
| Lateral | Linea aspera and the lateral fusion of the middle and deep gluteal fascia |
| Superior | Inferior margin of the sciatic notch |
| Inferior | Hamstring origin |
| Contents | Piriformis, gemelli, obturator internus and externus, quadratus femoris, hamstring origin, sacrotuberous and sacrospinous ligaments, superior and inferior gluteal nerves and vessels, and the sciatic nerve |
Sciatic nerve–piriformis variants
Beaton and Anson described six relationships between the sciatic nerve and the piriformis. Their pooled frequencies across more than 6,000 dissected limbs are shown below. Variants are common in people without symptoms, so a variant is more convincing when the nerve on the same side shows abnormal signal and the clinical picture agrees with it.
Table 2. Beaton and Anson classification
| Type | Relationship | Approximate frequency |
|---|---|---|
| A | Undivided nerve passes below the piriformis (normal course) | 83.1% |
| B | Divided nerve: one division through, one below the muscle | 13.7% |
| C | Divided nerve: one division above, one below the muscle | 1.3% |
| D | Undivided nerve passes through the muscle | 0.5% |
| E | Divided nerve: one division through, one above the muscle | 0.08% |
| F | Undivided nerve passes above the muscle | 0.08% |
Causes of deep gluteal syndrome
The sciatic nerve can be entrapped at any level as it travels from the sciatic notch to the hamstring origin. Thinking of the causes from top to bottom is a useful way to link symptoms, examination findings and imaging to a specific level.
The entrapment map, from proximal to distal
Sciatic notch / below the piriformis
Gemelli–obturator internus
Quadratus femoris / ischiofemoral space
Ischial tuberosity / hamstring origin
Each of the main causes is described below:
1. Piriformis syndrome
2. Ischiofemoral impingement (quadratus femoris syndrome)
Special situation: buttock or groin pain after hip replacement
Ischiofemoral impingement after total hip arthroplasty is linked mainly to increased femoral stem anteversion, or a large change in anteversion compared with the native hip. Other contributors are a cup placed too far medially and abductor dysfunction. On MRI with metal-artefact reduction, the proposed thresholds after arthroplasty are an ischiofemoral space ≤15 mm or quadratus femoris space ≤10 mm, together with quadratus femoris oedema or fatty atrophy. Infection and loosening must be excluded first.
The main alternative is iliopsoas impingement, compared below.
Table 3. Iliopsoas impingement vs ischiofemoral impingement after hip arthroplasty
| Feature | Iliopsoas impingement | Ischiofemoral impingement |
|---|---|---|
| Pain location | Anterior groin, sometimes anterior thigh | Lower buttock, groin or medial thigh |
| Provoked by | Active hip flexion (stairs, getting into a car), painful snapping | Long strides, extension with adduction; eases with a shorter stride |
| Key examination | Pain on resisted hip flexion or seated SLR | Long-stride walking test, IFI test |
| Main implant factor | Anterior cup overhang or oversized cup | Increased stem anteversion; cup placed too far medially |
| Key imaging | CT for cup overhang (>4 mm); ultrasound for tendinitis or bursitis | MRI with metal-artefact reduction; CT torsion study |
| Confirming injection | Iliopsoas sheath or bursa | Ischiofemoral space or quadratus femoris |
3. Gemelli–obturator internus syndrome
4. Proximal hamstring (ischial tunnel) syndrome
5. Fibrous and fibrovascular bands
6. Less common causes
Table 4. Less common causes of deep gluteal syndrome and their clues
| Category | Examples | Key clue |
|---|---|---|
| Vascular | Gluteal or persistent sciatic artery aneurysm or pseudoaneurysm, varices, sciatic notch hernia | Pulsatile mass, previous trauma or intervention, changes on MRN |
| Tumours and pseudotumours | Nerve sheath tumours, lipoma, sarcoma, metastases, ganglion cyst, haematoma | Night or rest pain, progressive deficit, history of cancer, palpable mass |
| Gynaecological | Endometriosis of the sciatic nerve | Cyclical sciatica |
| After surgery or trauma | Hip arthroplasty, hardware, heterotopic ossification, fracture malunion, post-surgical scarring | Onset after a procedure or injury |
| Inflammatory or infective | Pyomyositis, abscess, inflammatory myositis | Fever, immunosuppression, injecting drug use, raised inflammatory markers |
| Other nerves | Pudendal, posterior femoral cutaneous, and cluneal nerves (the cluneal nerves are entrapped at the iliac crest) | Pudendal: perineal pain on sitting, relieved on a toilet seat. Posterior femoral cutaneous: purely sensory buttock and posterior thigh pain. Cluneal: “pseudo-sciatica” that responds to a block at the iliac crest. |
Pinpointing the culprit: side-by-side comparison
Table 5. The main causes of deep gluteal syndrome compared
| Feature | Piriformis | Gemelli–OI | IFI (quadratus femoris) | Proximal hamstring | Fibrous bands |
|---|---|---|---|---|---|
| Where it hurts | Upper buttock, sciatic notch | Mid deep buttock | Lower buttock lateral to ischium; groin | Ischial tuberosity, posterior thigh | Variable, depending on level |
| Provoked by | Sitting; flexion, adduction and internal rotation | Resisted external rotation in neutral or extension | Long strides; extension with adduction | Sitting on the sit bone; resisted knee flexion | Nerve-gliding movements |
| Best bedside test | Active piriformis + seated stretch | No validated test | Long-stride walking; IFI test | Resisted knee flexion at 30° and 90° | No specific test |
| Imaging | Enlarged piriformis on one side + nerve hyperintensity | Usually normal | Narrowed spaces; quadratus femoris oedema or atrophy | Tendon disease; nerve change at ischium | Perineural fibrosis; often occult |
| Confirm with | Piriformis belly injection | Clinical; endoscopic | Ischiofemoral space injection | Peritendinous injection | Often endoscopic |
Localising flowchart: which structure is it?
Worse sitting, FAIR / active piriformis test positive
→ Piriformis
Imaging normal
→ Gemelli–obturator internus
Long-stride / IFI test positive
→ Ischiofemoral impingement
Ischial tenderness, resisted knee flexion painful
→ Proximal hamstring
Pain on nerve-gliding movements, previous trauma or surgery
→ Consider fibrous bands
Remember
These causes can coexist, and ischiofemoral impingement can irritate the sciatic nerve in its own right. Nerve symptoms alone therefore do not point to any one structure.
Clinical presentation
Symptoms are often vague and overlap with lumbar, hip and pelvic conditions, which is why DGS is often recognised late. The most common features are:
- deep buttock or retro-trochanteric pain and tenderness, usually one-sided but sometimes on both sides
- sciatica-like pain or paraesthesia radiating down the posterior thigh, occasionally to the foot
- inability to sit for more than 20–30 minutes, with driving a typical trigger
- night pain, limping, and pain made worse by hip rotation in flexion with the knee extended
- an antalgic sitting posture, shifting weight onto the other buttock
Low back pain may be present but is not usually prominent. True root-level neurological deficits (myotomal weakness, reflex loss or dermatomal sensory loss) should prompt a search for a spinal cause.
Examination: the key bedside tests
No single test is diagnostic. Combinations perform better than individual tests, and test accuracy figures assume that spinal causes and limb malalignment have already been excluded.
Table 6. Provocative tests for deep gluteal syndrome and its subtypes
| Test | How to perform | Positive if | Accuracy (sens / spec) |
|---|---|---|---|
| Active piriformis test | Patient lies on the unaffected side, pushes the heel into the table, then abducts and externally rotates against resistance while the examiner palpates the piriformis | Pain reproduced at the sciatic notch | 0.78 / 0.80 |
| Seated piriformis stretch test | Seated, hip flexed to 90°, knee extended. The examiner moves the hip passively into adduction and internal rotation, palpating 1 cm lateral to the ischium and at the sciatic notch | Posterior pain reproduced | 0.52 / 0.90 Combined with the active test: 0.91 / 0.80 |
| FAIR | Hip flexion, adduction and internal rotation, which narrows the space between the piriformis, superior gemellus and sacrotuberous ligament | Buttock or sciatic pain | Not well established |
| Freiberg sign | Forceful internal rotation of the extended thigh | Buttock pain | Not well established |
| Pace sign | Resisted abduction and external rotation in the seated position | Pain or weakness | Not well established |
| Beatty manoeuvre | Side-lying on the unaffected side; the patient lifts the flexed knee off the table | Deep buttock pain suggests DGS; back and leg pain suggests a disc problem | Not well established |
| Long-stride walking test | Patient walks taking long strides, then short strides | Posterior hip pain as the affected hip extends, relieved by short strides | 0.94 / 0.85 (IFI) |
| IFI test | Side-lying; passive hip extension in adduction, then in abduction | Pain in adduction, relieved in abduction | 0.82 / 0.85 (IFI) |
| Resisted knee flexion | Resisted knee flexion at 30° and at 90° | Pain at the hamstring origin | Specificity 0.97, LR+ 26.9 (hamstring) |
| Straight-leg raise | Standard SLR | Radicular pain | Only 0.15 sensitive for endoscopically confirmed entrapment |
Practical examination tips
- A positive SLR does not automatically mean a disc problem. A clear dermatomal or myotomal deficit favours the spine. Isolated notch tenderness with positive piriformis tests favours DGS.
- Compare the key tests directly. A positive FAIR or active piriformis test with a negative long-stride test points to the piriformis; the reverse points to the quadratus femoris.
- Always screen for mimics: sacroiliac provocation tests (three or more positive suggests SIJ pain), palpation of the hamstring origin, and hip range of motion for intra-articular disease.
Differential diagnosis and red flags
Table 7. Lumbar radiculopathy vs deep gluteal syndrome vs ischiofemoral impingement
| Feature | Lumbar radiculopathy | Deep gluteal syndrome | Ischiofemoral impingement |
|---|---|---|---|
| Pain location | Back pain plus leg pain in an L4, L5 or S1 dermatome, often reaching the foot | Deep buttock, sometimes radiating down the posterior thigh | Deep buttock lateral to the ischial tuberosity; sometimes groin |
| Aggravating factors | Coughing, sneezing, sitting, changes of posture | Sitting >30 minutes, walking, night pain | Long strides, running, hip extension |
| Neurological examination | Weakness, sensory loss and reflex change fitting one root | Usually no root-level deficit | Usually normal |
| SLR | Sensitive (0.92) but not specific (0.28); crossed SLR specific (0.90) | May be positive, but insensitive | Does not discriminate |
| Key tests | Slump test (0.84–0.91 / 0.70–0.83) | Active piriformis + seated stretch; notch tenderness; Pace; FAIR | Long-stride walking test; IFI test |
Table 8. Mimics to exclude
| Condition | Pointers |
|---|---|
| Sacroiliac joint pain | Pain at or below the PSIS; three or more positive provocation tests (distraction, compression, thigh thrust) |
| Hip joint disease (labral tear, FAI, OA) | Groin pain, “C sign”, loss of internal rotation, pain on FADIR |
| Greater trochanteric pain syndrome / gluteal tendinopathy | Lateral hip pain, pain lying on the affected side, trochanteric tenderness |
| Axial spondyloarthritis | Alternating buttock pain, morning stiffness, onset before 45, improves with exercise |
| Cluneal or pudendal nerve entrapment | Iliac crest “pseudo-sciatica”; perineal pain on sitting |
Red flags: do not miss
- Cauda equina syndrome: saddle anaesthesia, sphincter disturbance, or bilateral or progressive deficits. Needs emergency MRI and surgical review.
- Malignancy: history of cancer, weight loss, night or rest pain, palpable mass. Needs pelvic and spinal MRI with contrast.
- Infection: fever, immunosuppression, injecting drug use. Check blood count and inflammatory markers, and arrange contrast MRI.
Investigations
No single imaging finding confirms DGS. Imaging is used to exclude other causes, to localise the problem and to find a cause, and is interpreted together with the examination. Investigations are generally reserved for persistent or disabling symptoms.
- Lumbar spine MRI first, to exclude a discogenic or other spinal cause.
- Pelvic MRI or MR neurography of both sides. MRN uses heavily T2-weighted, fat-suppressed sequences, ideally at 3T. It is the best way to show nerve involvement and to map the site of entrapment. Axial T1 and T2 fat-saturated images should run from the sciatic notch to the ischial tuberosity, with measurement of the ischiofemoral and quadratus femoris spaces.
- High-resolution and dynamic ultrasound shows dynamic impingement and guides injections.
- Electrodiagnostics (H-reflex latency on FAIR, EMG denervation) give variable results. They are most useful when there is a motor deficit and are often normal in mild entrapment.
- Selective image-guided diagnostic injection is the most practical functional confirmation, since imaging abnormalities are common in people without symptoms.
Table 9. MRI and MR neurography: deep gluteal sciatic entrapment vs ischiofemoral impingement
| Feature | Sciatic entrapment (DGS) | Ischiofemoral impingement |
|---|---|---|
| Main abnormality | The nerve itself: asymmetric T2 hyperintensity, swelling, fascicular oedema, loss of fat around the nerve | Muscle and bone: quadratus femoris oedema (acute) or atrophy (chronic) |
| Location | Sciatic notch or below the piriformis; ischial tuberosity if hamstring-related | Between the lateral ischial tuberosity and the lesser trochanter |
| Measurements | Not diagnostic | Ischiofemoral space <17 mm (range 15–20); quadratus femoris space <8 mm (range 7–10) |
| Visible cause | Enlarged piriformis on one side, accessory head, nerve through the muscle, bands or scarring, haematoma, pseudoaneurysm, mass | Narrowed space, often with increased femoral anteversion or a wider neck–shaft angle |
| What MRN adds | Shows nerve change next to the compressing structure, mapping the target for injection or surgery | Shows any secondary sciatic irritation behind the quadratus femoris |
Interpretation pitfalls
- Piriformis variants are common in people without symptoms. They are more convincing when nerve signal on the same side is abnormal.
- Quadratus femoris oedema does not equal symptomatic IFI. In adults with an ischiofemoral space under 15 mm, oedema was present in 84% but did not correlate with pain. Normal and abnormal spaces overlap (control means 17.6–30.6 mm), and measurements change with hip position. Compare both sides, and exclude a simple muscle strain.
- Gemelli–obturator internus compression is dynamic and usually invisible on static imaging.
“An anatomical variant on a scan is not a diagnosis. I place far more weight on a careful examination and a well-placed, single-target diagnostic injection. If injecting one structure takes the pain away, we know where to focus treatment.”
Table 10. Proposed diagnostic criteria for piriformis syndrome (Han et al.)
| Criterion |
|---|
| 1. Deep-seated buttock pain with radiating pain, especially intolerable pain on sitting |
| 2. Tenderness of the piriformis muscle |
| 3. Positive provocative test (Freiberg or Pace) |
| 4. Positive CT or MRI findings: asymmetry or enhancement around the sciatic nerve |
| 5. Pain relief with a local anaesthetic or steroid injection |
| Diagnosis is made when 4 or more criteria are present, after excluding spinal and pelvic pathology |
Flowchart 1. Diagnostic pathway for suspected deep gluteal syndrome
Management
Most cases are benign and settle once provoking factors are avoided. A wide range of treatments has been used, but most studies are small and poorly controlled. A stepwise approach, matched to the likely culprit structure, is sensible.
Flowchart 2. Stepwise management
Education, avoiding provoking postures and activities, simple analgesia or NSAIDs, neuropathic agents where appropriate, and structured physiotherapy (stretching, hip strengthening, nerve mobilisation)
Local anaesthetic ± corticosteroid into the target structure (piriformis, ischiofemoral space, hamstring origin). Diagnostic and therapeutic; continue rehabilitation
Mainly for confirmed piriformis syndrome; off-label
Endoscopic sciatic nerve release, or lesser trochanter resection for IFI
Conservative care
- Education and load modification: limit prolonged sitting (use a cushion, take regular breaks, remove a back-pocket wallet) and avoid provoking activities. For IFI, shorten the stride, avoid overstriding and hill running, and avoid crossing the legs or standing with the hip “hanging” in adduction.
- Movement retraining: correct dynamic hip adduction, contralateral pelvic drop and excessive anterior pelvic tilt, all of which narrow the deep gluteal and ischiofemoral spaces.
- Medication: a short course of NSAIDs if appropriate, muscle relaxants, and neuropathic pain agents for prominent neural symptoms.
- Physiotherapy: piriformis stretching, gluteal and core strengthening, and nerve mobilisation, as outlined below.
Exercise selection: strengthening gluteus medius without loading the piriformis
Exercises that combine hip abduction with neutral or internal rotation, with the hip extended, produce strong gluteus medius activation without the external rotation component that recruits the piriformis. This selection is based on EMG and functional MRI studies in healthy people. No study has measured piriformis load in patients with piriformis syndrome.
Table 11. Exercise selection in deep gluteal syndrome
| Preferred early (high gluteus medius, low piriformis demand) | Use with caution early (recruit the deep rotators) |
|---|---|
| Side-lying hip abduction with internal rotation: highest-ranked for gluteus medius activation (about 73% MVC) | Clamshell: highest obturator internus activation, with relatively low gluteus medius activity (about 26%) |
| Plain side-lying hip abduction: about 54–70% MVIC; adding external rotation shifts the work to the TFL | Side-lying abduction with external rotation: activates all the deep gluteal muscles most |
| Prone heel squeeze and double-leg bridge with abdominal bracing | Single-leg bridge: strong gluteal work, but also activates the piriformis (a sacroiliac stabiliser); progress from double-leg bridges |
| Later: side plank (heavy quadratus lumborum load), loaded single-leg squat, single-leg Romanian deadlift | Reintroduce external rotation work once FAIR provocation has settled. Regress any exercise that reproduces buttock or sciatic pain |
Sciatic nerve gliding
No controlled trials have tested nerve gliding specifically in piriformis syndrome or DGS. Its use is extrapolated from neural mobilisation studies in low back pain and sciatica. These show modest, mostly short-term benefits when gliding is part of a broader programme, and the certainty of that evidence is very low. It is therefore best used as an add-on rather than a main treatment.
- Start with sliders, which load one end of the nerve while unloading the other and are gentler on an irritable nerve. An example is a seated slump slider, extending the knee with the neck extended, then flexing both. Do 10–15 pain-free repetitions, 1–3 times a day.
- Add a hip flexion–adduction–internal rotation bias once FAIR-position irritability has settled, to target the nerve below the piriformis.
- Progress to tensioners only if sliders are well tolerated.
- Stop or regress if paraesthesia or pain lasts more than a few minutes after a session or if any neurological deficit appears. Avoid aggressive tensioning when severe compression (mass, dense bands, progressive deficit) is suspected.
Image-guided injections
Injections of local anaesthetic, with or without corticosteroid, under ultrasound or CT guidance are both diagnostic and therapeutic. The technique matters if the result is to mean anything:
- Target one structure at a time (piriformis belly, ischiofemoral space or quadratus femoris, hamstring origin), using a small volume to avoid spread to neighbouring structures.
- Record pain scores on the provocative tests before and after the injection.
- Interpret with care. Relief from injecting only the target muscle is the most informative result. If the anaesthetic also reaches the sciatic nerve, relief no longer tells you which structure was responsible.
Relief is often short-lived, but a positive block is valuable: it supports the diagnosis and selects patients for botulinum toxin or, rarely, surgical referral. The evidence base for piriformis injections is weak, and there is no formal guideline recommendation.
Botulinum toxin for piriformis syndrome
Botulinum toxin is an off-label, second-line option. It blocks presynaptic acetylcholine release, producing temporary weakness and atrophy of the piriformis. It is best suited to patients who:
- have persistent or recurrent symptoms despite several weeks of physiotherapy, and
- have had a positive piriformis-only diagnostic block that gave only brief relief, or have electrophysiological confirmation (the main RCT required H-reflex prolongation of at least 1.86 ms on FAIR), and
- ideally, have supporting imaging such as an enlarged piriformis or nerve signal change.
In a 2022 meta-analysis, botulinum toxin outperformed placebo and was broadly comparable to local anaesthetic or steroid alone. Local anaesthetic plus steroid performed best overall. The evidence quality is moderate at best.
Table 12. Botulinum toxin doses used in published studies
| Product | Dose / dilution | Technique | Evidence |
|---|---|---|---|
| IncobotulinumtoxinA | 300 U in 3 mL saline; 75 U at each of 4 sites | EMG-guided; plus 12 weeks of physiotherapy | RCT (n=56): better pain and H-reflex outcomes than saline plus physiotherapy |
| OnabotulinumtoxinA | 300 U at 4 sites, about 2 mL total | EMG motor point; physiotherapy twice weekly for 12 weeks | Early controlled study |
| OnabotulinumtoxinA | 100 U in 2 mL; repeated as 100 U in 5 mL on relapse | Single injection into the muscle | Case report: 2 years of relief after the more dilute repeat dose |
Units are product-specific and cannot be converted between products. The optimal dose has not been established. Lower doses reduce systemic exposure and the risk of distant spread. Repeat injections are generally given no sooner than every 12 weeks.
Practical points for botulinum toxin
- Targeting: cadaver mapping shows the densest intramuscular nerve branching between one-fifth and two-fifths of the distance from the lateral sacral border to the greater trochanter. Lateral to this the muscle is largely tendinous. Inject under image guidance into this zone and away from the sciatic nerve.
- Contraindications and cautions: myasthenia gravis, Lambert–Eaton syndrome, motor neurone disease, hypersensitivity, injection-site infection and pregnancy. Use caution with aminoglycosides or neuromuscular blocking agents.
- Adverse effects: temporary weakness of neighbouring hip rotators or gluteals (watch gait and falls risk in older patients), injection pain, flu-like symptoms, and rarely distant spread (dysphagia, generalised weakness). Count the total dose given at all sites within 3 months.
- Always pair with rehabilitation. Treat the toxin as opening a window for rehabilitation, not as a stand-alone treatment.
“Injections, including botulinum toxin, work best as a window for rehabilitation. The long-term results come from the exercise programme that follows.”
Table 13. Phased rehabilitation after piriformis botulinum toxin (adapted from trial regimens)
| Phase | Focus |
|---|---|
| Weeks 0–2 (effect begins at 3–7 days) |
Start physiotherapy within days. Heat before gentle supine and standing piriformis stretches in the FAIR position, progressed as tolerated. Soft-tissue work (avoid vigorous massage over injection sites for the first day or so), nerve sliders, pain-limited walking. |
| Weeks 2–6 (peak effect) |
Progress to deeper stretches. A CT modelling study found about 115–120° hip flexion with 40–50° external rotation and 25–30° adduction lengthened the piriformis 30–40% more than conventional stretches. Begin lumbopelvic stabilisation and the preferred gluteus medius exercises. |
| Weeks 6–12 | Hip abductor and extensor strengthening, gait and sitting posture retraining, sport-specific rehabilitation. Move to a self-directed home programme before the toxin wears off at around 10–12 weeks. |
Reassess pain, FAIR provocation and function every 2 weeks. No trial has compared different physiotherapy regimens after toxin injection; this programme is based on trial co-interventions and expert practice.
Surgery: a brief note
Surgery is reserved for a small minority with persistent, disabling symptoms despite adequate conservative care and an injection-confirmed diagnosis, or where a mass or vascular lesion is compressing the nerve. Options include endoscopic sciatic nerve decompression (release of fibrous bands and of the piriformis or obturator internus tendon as needed) and, for ischiofemoral impingement, endoscopic partial resection of the lesser trochanter or, with structural deformity, femoral derotation osteotomy. Reported outcomes are encouraging; in one series of 52 hips, 39 had good to excellent results. However, the evidence comes entirely from case series, and these procedures require specialist hip endoscopy expertise.
The Pain Spa approach
At Pain Spa, patients referred with “sciatica” that does not fit the spinal picture are assessed by Dr Murli Krishna, Consultant in Pain Medicine. Assessment combines a structured examination of the deep gluteal space, review of spinal and pelvic imaging, and, where appropriate, precise image-guided diagnostic injections to identify the structure responsible. Dr Krishna has extensive experience of image-guided injection across a wide range of pain conditions. Treatment is then matched to the specific cause and delivered alongside a structured rehabilitation plan, working closely with referring clinicians and physiotherapists.
Explaining it to patients:
“Your sciatic nerve is the large nerve that runs from your lower back, through your buttock and down the back of your leg. Usually sciatica comes from a problem in the spine. In your case, the nerve seems to be getting squeezed or caught deep in the buttock, by a tight or enlarged muscle, by narrowing between two bones, or by bands of scar-like tissue.”
“That is why sitting for a long time, or certain hip movements, bring on your pain. The good news is that most people improve with changes to how they sit and move, and a targeted exercise programme.”
“If that is not enough, a precisely guided injection can both confirm where the problem is and ease the pain while you continue your exercises. Surgery is only needed rarely.”
Glossary
| DGS | Deep gluteal syndrome: non-discogenic sciatic nerve entrapment in the subgluteal space |
| IFI | Ischiofemoral impingement: narrowing between the ischial tuberosity and the lesser trochanter, compressing the quadratus femoris |
| IFS / QFS | Ischiofemoral space / quadratus femoris space, measured on axial MRI |
| MRN | MR neurography: heavily T2-weighted, fat-suppressed imaging of peripheral nerves |
| FAIR | Flexion, adduction and internal rotation of the hip, which stretches the piriformis |
| FADIR | Flexion, adduction and internal rotation test for intra-articular hip pathology |
| Freiberg sign | Pain on forceful internal rotation of the extended thigh |
| Pace sign | Pain or weakness on resisted abduction and external rotation in sitting |
| Ischial tunnel syndrome | Sciatic nerve entrapment at the hamstring origin |
| Sliders / tensioners | Nerve mobilisation techniques that glide the nerve (sliders) or load both ends at once (tensioners) |
| MVC / MVIC | Maximum voluntary (isometric) contraction, the reference for EMG activation percentages |
Selected references
- Hernando MF, Cerezal L, Pérez-Carro L, et al. Deep gluteal syndrome: anatomy, imaging, and management of sciatic nerve entrapments in the subgluteal space. Skeletal Radiol 2015;44:919–34.
- Perez Carro L, Fernandez Hernando M, Cerezal L, et al. Deep gluteal space problems: piriformis syndrome, ischiofemoral impingement and sciatic nerve release. Muscles Ligaments Tendons J 2016;6(3):384–96.
- Pearce JMS. The deep gluteal (piriformis) syndrome. Adv Clin Neurosci Rehabil 2024;22(3):22–3.
- Martin HD, Kivlan BR, Palmer IJ, Martin RL. Diagnostic accuracy of clinical tests for sciatic nerve entrapment in the gluteal region. Knee Surg Sports Traumatol Arthrosc 2014;22(4):882–8.
- Kizaki K, Uchida S, Shanmugaraj A, et al. Deep gluteal syndrome is defined as a non-discogenic sciatic nerve disorder with entrapment in the deep gluteal space: a systematic review. Knee Surg Sports Traumatol Arthrosc 2020.
- Park JW, Lee YK, Lee YJ, et al. Deep gluteal syndrome as a cause of posterior hip pain and sciatica-like pain. Bone Joint J 2020.
- Smoll NR. Variations of the piriformis and sciatic nerve with clinical consequence: a review. Clin Anat 2010;23(1):8–17.
- Bartret AL, Beaulieu CF, Lutz AM. Is it painful to be different? Sciatic nerve anatomical variants on MRI and their relationship to piriformis syndrome. Eur Radiol 2018;28(11):4681–6.
- Stewart JD. The piriformis syndrome is overdiagnosed. Muscle Nerve 2003;28(5):644–6.
- Han SK, Kim YS, Kim TH, Kang SH. Surgical treatment of piriformis syndrome. Clin Orthop Surg 2017;9(2):136–44.
- Hernando MF, Cerezal L, Pérez-Carro L, et al. Evaluation and management of ischiofemoral impingement: a pathophysiologic, radiologic, and therapeutic approach to a complex diagnosis. Skeletal Radiol 2016.
- Bucknor MD, Steinbach LS, Saloner D, Chin CT. Magnetic resonance neurography evaluation of chronic extraspinal sciatica after remote proximal hamstring injury. J Neurosurg 2014;121(2):408–14.
- Fishman LM, Wilkins AN, Rosner B. Electrophysiologically identified piriformis syndrome is successfully treated with incobotulinum toxin A and physical therapy. Muscle Nerve 2017;56(2):258–63.
- Bateman EA, Fortin CD, Guo M. Musculoskeletal mimics of lumbosacral radiculopathy. Muscle Nerve 2025.
- Fischer T, Stern C, Fritz B, et al. MRI findings of ischiofemoral impingement after total hip arthroplasty are associated with increased femoral antetorsion. Acta Radiol 2022.
- Mohorea MA, Macdougall F, Cohen D, et al. Surgical management results in lasting pain relief in patients with ischiofemoral impingement refractory to nonoperative treatment: a systematic review. Curr Rev Musculoskelet Med 2026.
This article is intended for healthcare professionals and is for educational purposes only. It does not replace individual clinical assessment. Botulinum toxin use for piriformis syndrome is off-label.